
Introduction
Candidiasis is a primary or secondary fungal infection that can be caused by different species of Candida. It can present acutely, subacutely, or chronically on different human surfaces, such as skin, nails, mucous membranes, and internal organs. Mucosal candidiasis is one of the most common types of this infection, which mainly affects the mucous membrane of the mouth and esophagus; moreover, several species of Candida, especially C. albicans, can cause this disease [ 1 - 3 ]. For the treatment of this fungal infection, various antifungal drugs, such as azoles, especially fluconazole, are used. In recent years, numerous reports have highlighted the resistance of C. albicans to this antifungal in various patients, which ultimately caused the failure of the treatment in these cases [ 4 , 5 ].
Various mechanisms cause the resistance of C. albicans to fluconazole, which includes changes in 14α-demethylase, increased production of 14α-demethylase, exit phenomenon, and changes in the ergosterol synthesis pathway. One of the genes that play an important role in the resistance mechanisms against fluconazole is ERG11. This gene encodes the 14α-demethylase enzyme, and the mutation in this gene reduces the affinity of 14α-demethylase to fluconazole, and by making structural changes in 14α-demethylase, it does not allow azole drugs to stick to this enzyme, thereby leading to resistance in fungi (Figure 1-A)[ 6 - 8 ]. Mutations in the UPC2 gene, which controls the expression level of the ERG11 gene, can increase the expression of the ERG11 gene and the number of its copies, eventually resulting in the overproduction of 14α-demethylase, which is considered another resistance mechanism to fluconazole in C. albicans (Figure 1-B) [ 9 - 10 ]. The CDR1, CDR2, and MDR1, which encode Candida membrane efflux pumps, are among the genes effective in resistance to azoles, especially fluconazole. The CDR1 and CDR2 encode the ATP-binding cassette (ABC) pumps, and MDR1 encodes the major facilitator superfamily pumps, which ultimately cause the release of toxic molecules, such as azole drugs from Candida cells. TAC1 and MRR1 genes control the expression of CDR1, CDR2, and MDR1 genes; in addition, the mutation in each of them will increase the expression of CDR1, CDR2, and MDR1, and as a result, increase resistance against azole drugs (Figure 1-C) [ 11 , 12 ].
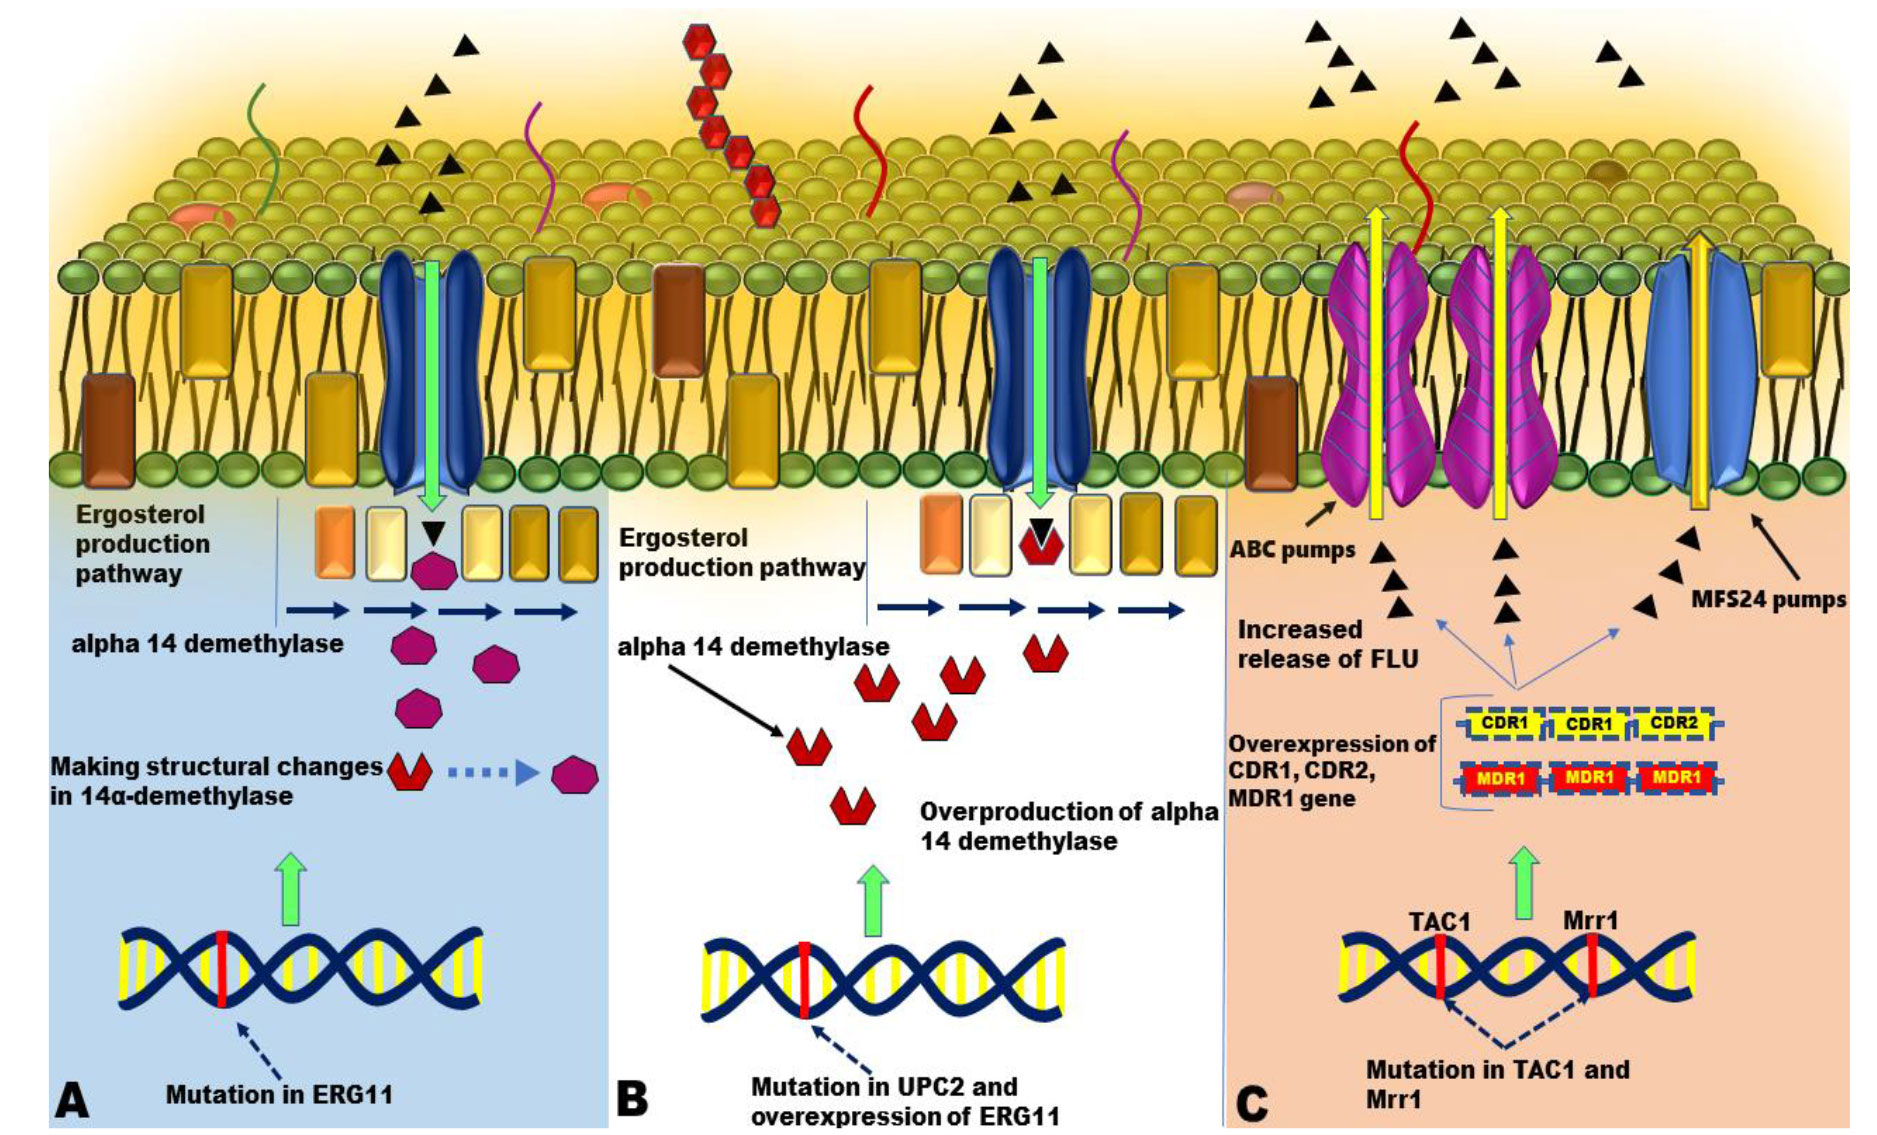
Figure 1.A. A mutation in the ERG11 gene (encoding the 14-alpha-deamylase enzyme) results in an amino acid substitution in the 14-alpha-deamylase protein sequence. These changes lead to a reduction in the affinity of 14-alpha-deamylase for azoles or to structural changes that prevent fluconazole from reaching the active site. Ultimately, it causes a resistant phenotype. B. Mutation in UPC2 and overexpression of ERG11 followed by overproduction of alpha-14 demethylase and resistance to fluconazole. C.TAC1 and MRR1 genes control the expression of CDR1, CDR2, and MDR1 genes. In addition, the mutation in each of them will increase the expression of CDR1, CDR2, and MDR1, and as a result, increase resistance against azole drugs.
Another gene involved in the resistance of Candida to azoles is ERG3. It should be noted that azole drugs, including fluconazole, by inhibiting the 14α-demethylase enzyme, cause the accumulation of 14α-methyl-3,6-diol in the C. albicans membranes, and these methylated sterols are converted by the enzyme delta 5-6 desaturase (encoded by ERG3). It becomes toxic to the products, and the accumulation of these toxic substances causes the death of the fungus. When a mutation occurs in the ERG3 gene, toxic products are not produced and C. albicans survive in the presence of fluconazole (Figure 2). This resistance mechanism has been shown experimentally by targeted deletion of the ERG3 gene in laboratory strains [ 13 , 14 ].
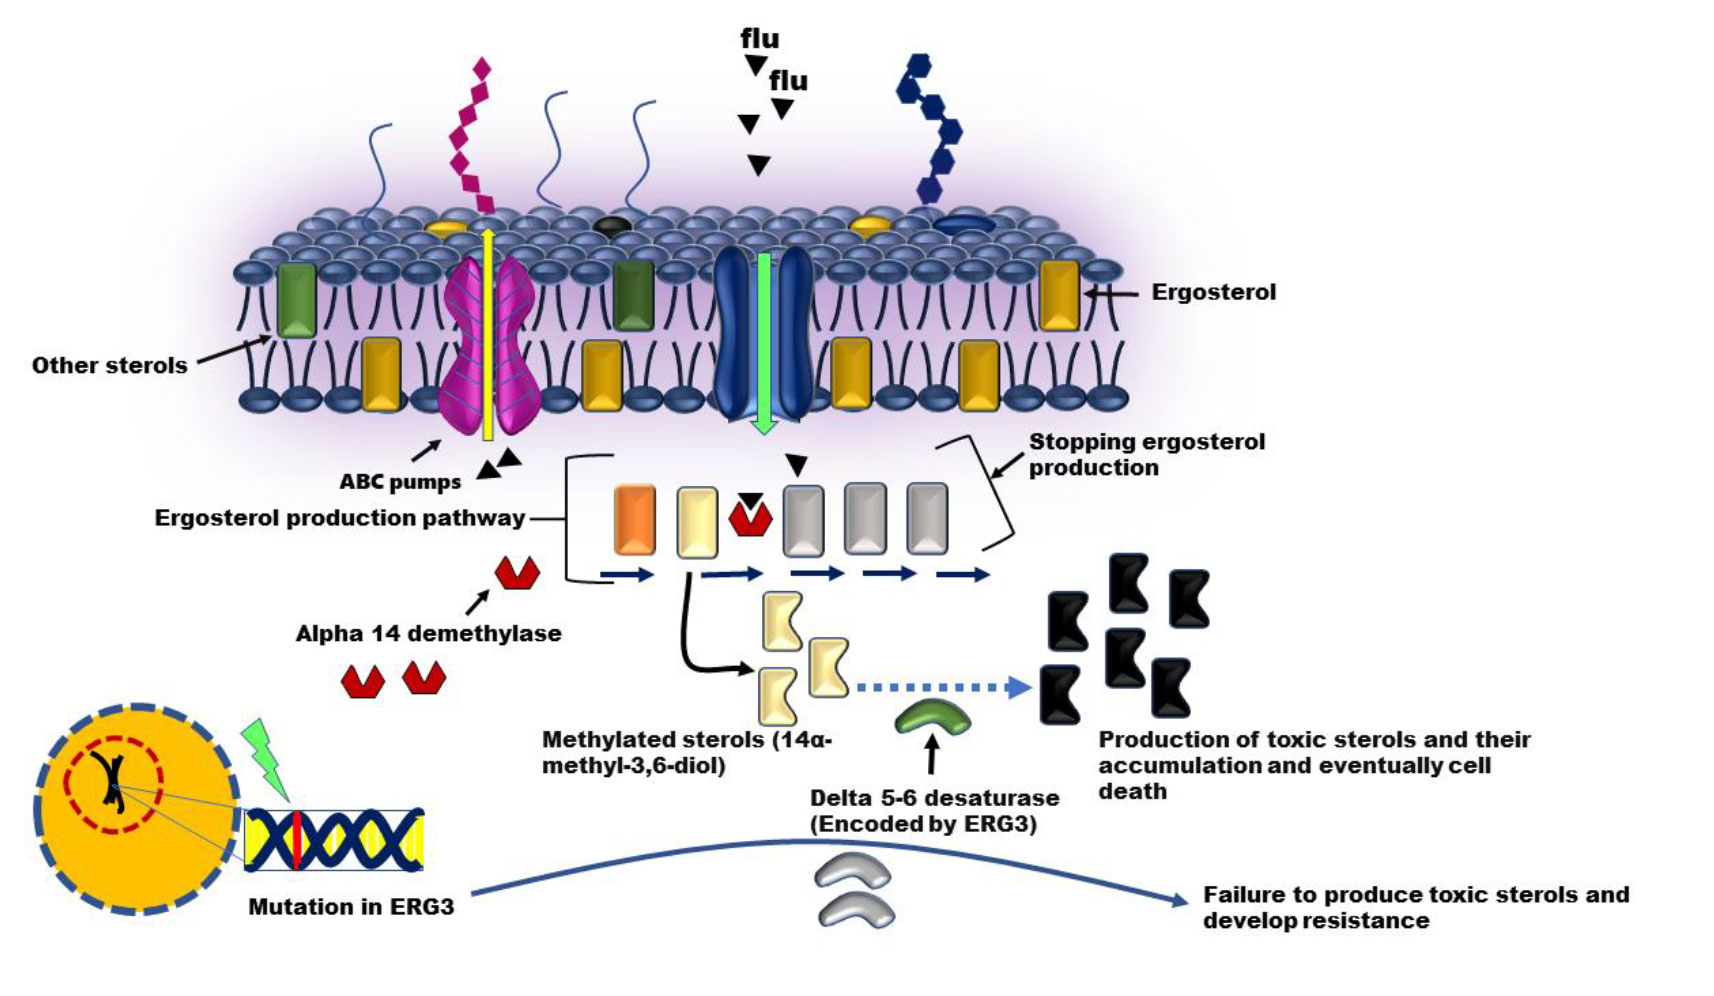
Figure 2. In the presence of fluconazole, inhibition of 14-alpha-deamylase leads to the accumulation of methylated sterols in the cell. These are then converted into toxic sterols by delta-5,6-desaturase (encoded by the ERG3 gene). If the ERG3 gene is mutated, these toxic products are no longer produced and the fungal cell survives and becomes resistant to fluconazole.
Besides genetic mutations or expression changes, environmental factors, such as host immune status, biofilm formation, efflux pumps, and environmental stressors (oxidative stress and nutrient limitation) play significant roles in modulating fluconazole resistance in Candida species [ 15 ]. The present study aimed to investigate the expression of genes involved in C. albicans resistance in people with different underlying diseases. By obtaining comprehensive information about the activity of these genes, the emergence of resistance to fluconazole and other azoles can be prevented, and appropriate treatment methods can be identified.
Materials and Methods
Literature search
In this systematic review with a comprehensive search conducted by three authors, several databases, such as PubMed (Medline), Scopus, and Web of Science were used to collect all studies evaluating the expression level of the key involved in C. albicans resistance to fluconazole from 1997 to 2024. The search in the mentioned databases was performed using a specific set of medical subject headings ("Resistance mechanisms" OR resistant OR "molecular mechanisms" OR "Drug resistance" OR resistance OR "efflux pumps" OR "ABC transporter" OR "resistant phenotype" OR "Efflux Mechanisms" OR "ATP-binding cassette" OR "drug efflux" ) AND ( fluconazole* OR "antifungal agents" OR "antifungal drugs" OR azole OR "azole resistance" OR "Subinhibitory concentrations") AND ("Candida albicans" OR candidiasis OR "oropharyngeal candidiasis" OR "vulvovaginal candidiasis") AND (cdr* OR erg11* OR mdr1 OR "Gene expression" OR overexpression OR mrr1/2 OR erg-11) keywords from February 1 to 28, 2023. It should be noted that in addition to the articles selected for the study, the references of these studies and related articles were also searched. The present review only used articles that were published in English.
Study selection criteria
The inclusion and exclusion criteria for the studies in this systematic review are as follows. All original English-language studies that were collected had three main criteria: 1) C. albicans isolates were collected from people with various underlying diseases associated with candidiasis, 2) the antifungal sensitivity of clinical C. albicans isolates to fluconazole was examined, and 3) the increased expression of fluconazole resistance genes in C. albicans isolates was investigated.
Regarding the exclusion criteria, studies were excluded if they met any of the following conditions: 1) focused on laboratory and non-clinical C. albicans isolates, 2) were published in other languages, including Turkish, Persian, Chinese, and Spanish, and 3) examined only the mutations that occurred in fluconazole-resistant C. albicans isolates, 4) investigated the increased expression of genes responsible for resistance to other azoles, except fluconazole, 5) worked on animal samples, such as mice, and 6) were narrative reviews, systematic reviews, meta-analyses, best evidence reviews, short letters or reports, case studies, book reviews, and book sections. Finally, 25 studies were selected and reviewed completely (Figure 3).
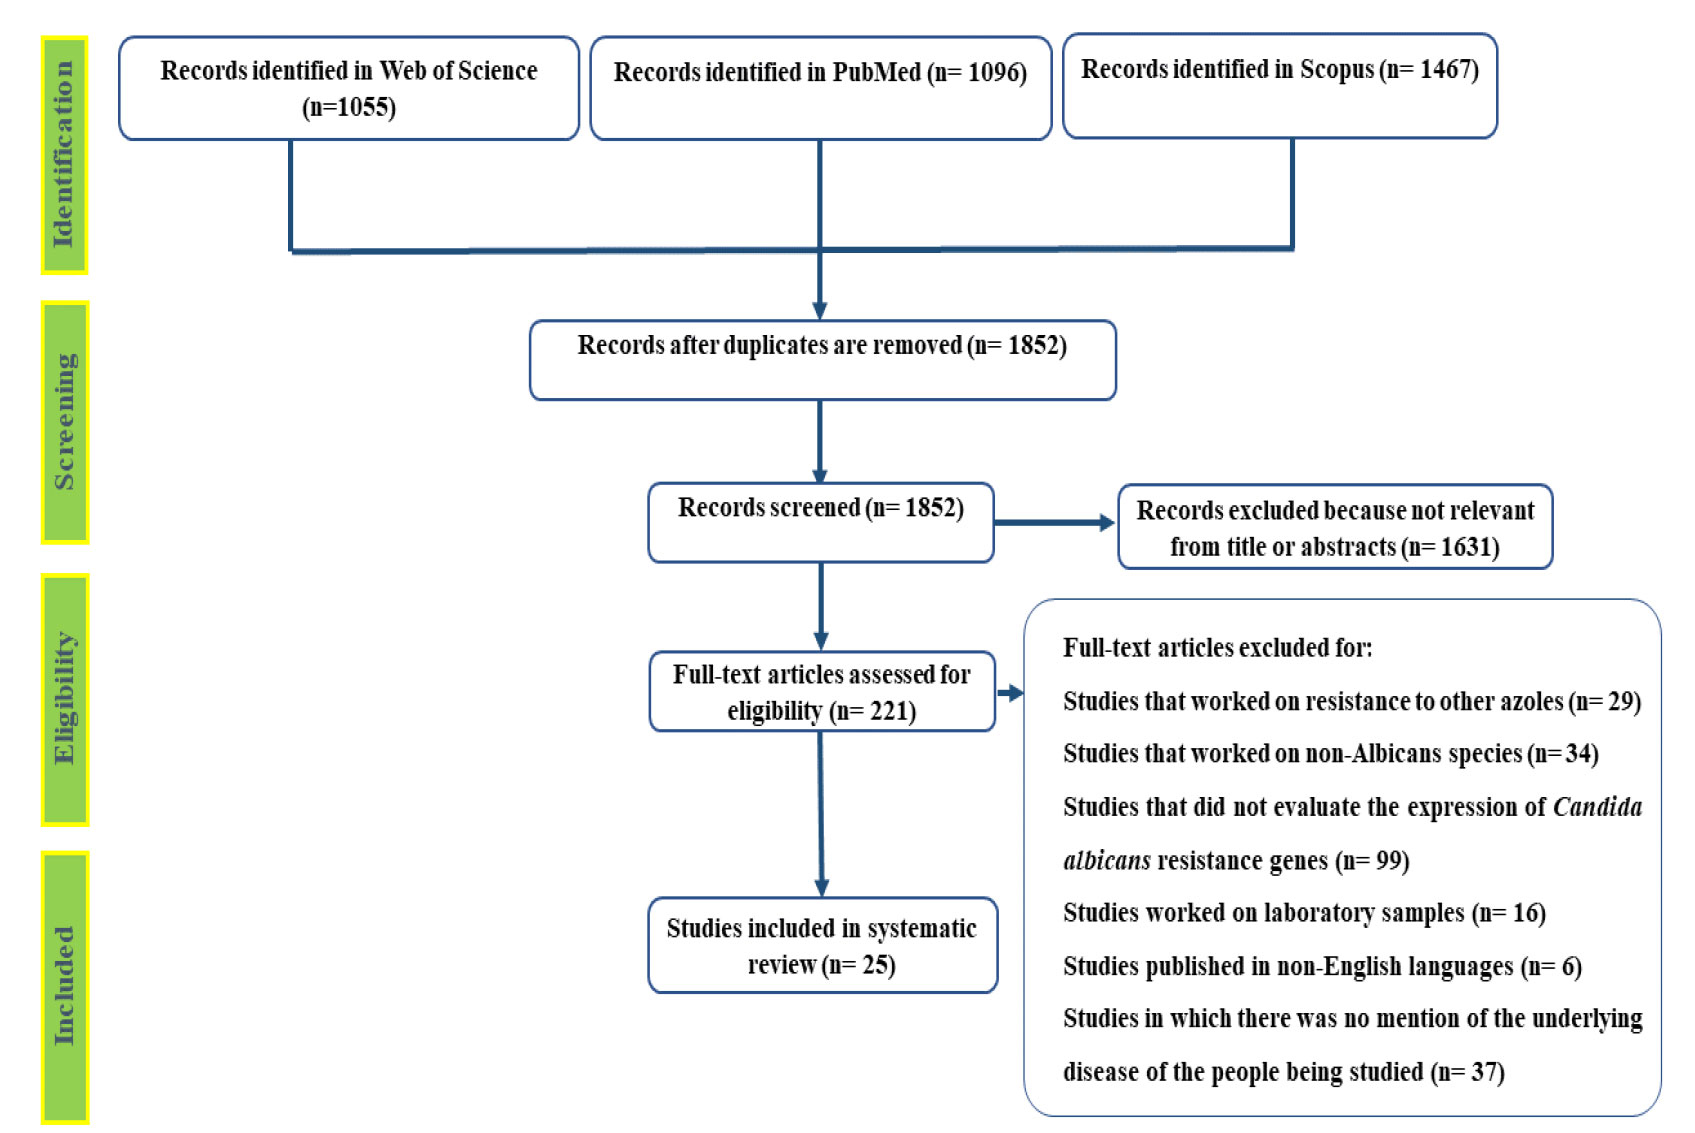
Figure 3. Flow diagram showing the study selection process.
This study was approved by the Ethics Committee of Ahvaz Jundishapur University of Medical Sciences Council (IR.AJUMS.REC.1402.197).
Results
Expression level of genes involved in C. albicans resistance to fluconazole in human immunodeficiency virus-infected patients
In recent years, the resistance of C. albicans to azole agents, particularly fluconazole, which is commonly used to treat oropharyngeal candidiasis in human immunodeficiency virus (HIV) patients, has resulted in treatment failure for these patients [ 41 ]. Based on the present research, 16 studies have been identified since 1995 that have examined the expression levels of genes responsible for fluconazole resistance in C. albicans isolated from HIV-infected patients.
Studies have revealed that most fluconazole-resistant C. albicans species are isolated from HIV-positive patients, many of whom have been on long-term fluconazole treatment during their therapy [ 42 , 43 ].
In HIV-infected patients, most fluconazole-resistant isolates exhibit lower levels of fluconazole intracellular accumulation than sensitive C. albicans strains. Among the studied genes, CDR1/2 genes were found to be the most highly expressed in fluconazole-resistant Candida species isolated from HIV-positive patients, followed by ERG11, MEDR1, BENr, and FLU1. However, it is essential to mention that some of these genes did not have overexpression in several fluconazole-resistant isolates, and in some cases, their expression even decreased. This contradiction could be due to the existence of different mechanisms of fluconazole resistance in C. albicans, as well as differences in the C. albicans strains examined in different studies. In the reviewed studies, CDR1 was found to be most significant in creating the resistant phenotype of Candida in HIV-positive patients (with an increase in expression from 2 to 17 times), followed by CDR2, CDR3, and CDR4, which were also investigated in some of these studies. However, unlike CDR1/2 genes, they were not associated with C. albicans resistance to fluconazole [ 18 , 23 ]. Another gene found to be highly involved in causing resistance was ERG11. The ERG11 gene was examined in 11 out of the 16 studies on C. albicans isolated from HIV-positive patients. In seven studies, there was an increase in the expression of this gene in resistant isolates [ 19 , 20 , 22 , 26 , 29 , 33 , 35 ], while in four studies the expression of ERG11 was not increased in any of the resistant isolates [ 23 , 25 , 27 , 36 ]. The MDR1 gene was not transcribed or barely transcribed in fluconazole-susceptible C. albicans strains. However, in most of the clinical isolates obtained from HIV-positive patients who were resistant to fluconazole, it was overexpressed, which eventually reduced the accumulation of fluconazole inside Candida cells and caused resistance to fluconazole. Some resistant strains of C. albicans in HIV-positive patients that did not overexpress CDR1 extensively expressed another efflux pump gene, BENr, which plays an important role in resistance [ 16 ]. Another gene involved in the resistance isolates was the FLU1 gene, which is a homologue of MDR1. Removal of this gene from several resistant C. albicans isolates increases their sensitivity to fluconazole. However, overexpression of this gene has not yet been suggested as a cause of fluconazole resistance in clinical isolates of C. albicans from HIV-infected patients [ 44 ].
The data from these 16 studies, conducted in different countries, such as the USA, Germany, and Japan, indicate that CDR1 followed by ERG11 genes play the most significant roles in creating the fluconazole-resistant phenotype. The genetic changes identified in this context suggest that the resistance of C. albicans to fluconazole develops in a stepwise manner and that one or more of these changes lead to the final resistant phenotype.
Expression level of genes involved in C. albicans resistance to fluconazole in cancer patients
In total, 2 out of 25 collected studies investigated the expression level of genes responsible for fluconazole resistance in C. albicans isolated from cancer patients [ 39 , 40 ]. Based on these two studies, the increase in the expression level of CDR1 and CDR2 genes in C. albicans isolated from these patients can cause resistance of C. albicans to fluconazole. However, CDR1 plays a greater role than CDR2 in this resistance.
According to a study performed by Maheronnaghsh et al., MDR1 is another gene found to be significantly over-expressed in fluconazole-resistant C. albicans isolated from cancer patients. Expression level of this gene is directly related to the level of resistance to fluconazole [ 39 ].
Maheronnaghsh et al. and Jahanshiri et al. noted that drugs used to treat certain cancers, such as cabazitaxel and idarubicin, which are also FDA-approved, have a negative effect on the antifungal activity of fluconazole. These drugs increase the expression of genes encoding drug-release proteins, such as MDR1 or ABC (CDR1 and CDR2), as well as the expression of the ERG11 gene, and ultimately increase the resistance of C. albicans to fluconazole by 4 to 16 times. Usage of some chemical drugs in people suffering from various types of malignancies can cause the C. albicans-resistant phenotype in this category of patients by affecting the expression level of the above-mentioned genes.
Expression level of genes involved in C. albicans resistance to fluconazole in organ transplant patients
According to Table 1, three studies have been conducted on C. albicans species isolated from transplant patients. In these individuals, as in HIV-infected and cancer patients, several genes play an essential role, and the combination of these genes leads to the emergence of C. albicans resistant phenotypes to fluconazole. In 2006, Xu et al. examined several resistant C. albicans species isolated from bone marrow transplant patients in terms of expression levels of resistance-causing genes. They found that CDR gene mRNA levels (including CDR1 and CDR2), as well as some genes involved in drug resistance, such as IFU5, RTA2, and IFD6, had increased 2.5 to 7 times, compared to sensitive species.
| No. | Author, year, country, and reference | Underlying disease | Isolated source | Evaluation of the expression of C. albicans resistance genes | Overexpression in C. albicans resistance genes |
|---|---|---|---|---|---|
| 1 | Sanglard et al. (1995) Switzerland [ 16 ] | HIV-infected patients | Oral or esophageal samples | CDR1, BENr | BENr (FC: ND), CDR1 (FC: ND) |
| 2 | White et al. (1997) USA [ 17 ] | HIV-infected patients | Oral samples | CDR1, ELF1, ERG1, ERG7, ERG16, HST6, PRD1, YCF1, MDR1 | ERG16 (FC: 4-5), CDR1 (FC: 5), MDR1 (FC: ND) |
| 3 | Franz et al. (1998) Germany [ 18 ] HIV-infected patients | Oral samples | CDR1, CDR2, CDR3, CDR4 | CDR1 (FC: 4.6), CDR2 (FC: 4 .6) | |
| 4 | Lopez-Ribot et al. (1998) USA [ 19 ] | HIV-infected patients | Oral or esophageal samples | ERG11, MDR1, CDR1, CDR2 | ERG11 (FC: ND), MDR1 (FC: ND), CDR1 (FC: ND), CDR2 (FC: ND) |
| 5 | Franz et al. (1998) Germany [ 20 ] | HIV-infected patients | Oral samples | CDR1, CDR2, MDR1, ERG11 | ERG11 (FC: ND), MDR1 (FC: ND) |
| 6 | Maesaki et al. (1999) Japan [ 21 ] | HIV-infected patients | Oral or esophageal samples | CDR1, MDR1 | CDR1 (FC: ND) |
| 7 | Perea et al. (2001) USA [ 22 ] | HIV-infected patients | Oral samples | CDR1, CDR2, MDR1, ERG11 | CDR1 (FC: ND), CDR2 (FC: ND), MDR1(FC: ND), ERG11 (FC: ND) |
| 8 | Maebashi et al. (2001) Japan [ 23 ] | HIV-infected patients | Oral samples | CDR1, CDR2, CDR3, CDR4, MDR2, ERG-11 | CDR1 (FC: ND), CDR2 (FC: ND) |
| 9 | Rogers et al. (2002) USA [ 24 ] | HIV-infected patients | Oral samples | CDR1, CDR2, MDR1, ERG11, RTA3, FET34, FTR2, MIR1, ERG2, GPI1, CWH8, GPX1, IFD5, ALD5, MDH1, MET3, LYS21, CRD2 | LYS21 (FC: 3.15), MDH1 (FC: 3.52), IFD5 (FC: 12.45), CRD2 (FC: 4.6), GPX1 (FC: 2.85), CWH8 (FC: 3.6), MIR1 (FC: 2.85), CDR1(FC: 3.67), ERG2(FC: 2.65) |
| 10 | Martinez et al. (2002) USA [ 25 ] | HIV-infected patients | Oral samples | ERG11, MDR1, CDR1, CDR2 | MDR1 (FC: ND), CDR1 (FC: ND), CDR2 (FC: ND) |
| 11 | Goldman et al. (2004) Brazil [ 26 ] | HIV-infected patients | Oral samples | ERG11, MDR1, CDR1, CDR2, FLU1 | ERG11 (FC: ND), MDR1 (FC: ND), CDR1 (FC: ND), CDR2 (FC: ND), FLU1 (FC: ND) |
| 12 | Ribeiro et al. (2005) Brazil [ 27 ] | HIV-infected patients | Vaginal samples | ERG11, MDR1, CDR1, CDR2 | CDR1 (FC: ND) |
| 13 | Xu et al. (2006) China [ 28 ] | Bone marrow transplantation patients | Blood culture samples | IPF7530, YOR1, PXA1, ALD5, GRP1, SOD2, IPF10565, CRD1, CDR2, CTR1, CTR2, CCC2, FET3, PDR16, IFD6, | CDR1 (FC: ND), CDR2 (FC: ND), IFU5 (FC: ND), RTA2 (FC: ND), IFD6 (FC: ND) |
| 14 | Dunkel et al. (2008) Germany [ 29 ] | HIV-infected patients | Oral samples | CDR1, CDR2, MDR1, UPC2, ERG11 | CDR1 (FC: ND), CDR2 (FC: ND), MDR1 (FC: ND), ERG11(FC: ND) |
| 15 | Sikhala et al. (2010) Finland [ 30 ] | APECED patients | Oral samples | CDR1, CDR2, TAC1, ERG1, MDR1 | CDR1 (FC: 9.8), CDR2 (FC: 20.4) |
| 16 | Mario et al. (2012) France [ 31 ] | HSCT recipient, heart transplant recipient | Respiratory tract, blood culture sample | ERG11, MDR1, CDR1, ERG3 | ERG11 (FC: 2.9 and 4.2) ** |
| 17 | Sikala et al. (2013) Finland [ 32 ] | APECED patients | Oral samples | CDR1, CDR2, | CDR1 (FC: ND), CDR2 (FC: ND) |
| 18 | Morio et al. (2013) France [ 33 ] | HIV-infected patients | Oral, respiratory tract, intra-abdominal sample | ERG11, MDR1, CDR1, | ERG11 (FC: ND), CDR1 (FC: ND), MDR1 (FC: 100) |
| 19 | Eddouzi et al. (2015) Tunisia [ 34 ] | Bone marrow transplantation patients | Oral swabs and blood culture samples | ERG11, MDR1 | ERG11 (FC: 2.7), MDR1 (FC: ND) |
| 20 | Rosana et al. (2015) Indonesia [ 35 ] | HIV-infected patients | Oral samples | ERG11, MDR1, CDR1, CDR2 | CDR1 (FC: 1.03– 2.8), CDR2 (FC: 1.4–121.1), MDR1(FC: 1.02–50.9), ERG11 (FC: 1.7–133.4) |
| 21 | Salari et al. (2015) Iran [ 36 ] | HIV-infected patients | Oral samples | CDR1, CDR2, MDR1, ERG11 | CDR1 (FC: ND), CDR2 (FC: ND), MDR1 (FC: ND) |
| 22 | Alizadeh et al. (2017) Iran [ 37 ] | Immunocompromised patients | Oral, vaginal, and cutaneous samples | ERG11 | * |
| 23 | Hiyama et al. (2021) Japan [ 38 ] | Diabetics patients | Urine sample | CDR1, CDR2, MDR1, ERG11 | CDR1 (FC: 2.5), CDR2 (FC: 8.5), MDR1(FC: 22.5), ERG11 (FC: 3.1) |
| 24 | Maheronnaghsh et al. (2022) Iran [ 39 ] | Cancer patients | Oral cavity and tongue samples | ERG11, MDR1, CDR1, CDR2 | CDR1 (FC: 1.79), MDR1 (FC: 9.64) |
| 25 | Jahanshiri et al. (2022) Iran [ 40 ] | Head and neck cancer patients | Oral samples | ERG11, MDR1, CDR1, CDR2 | MDR1 (FC:18.34-24.06), CDR1 (FC: 2), CDR2 (FC: 2), ERG11 (FC: 4.5-8) |
| FC: Fold Change, HIV: human immunodeficiency virus, APECED: Autoimmune polyendocrinopathy-candidiasis-ectodermal dystrophy, HSCT: Hematopoietic stem cell transplant *: Genes without overexpression **: Increased expression of resistance genes was measured in only two isolates. One showed a 2.9-fold increase, the other a 4.2-fold increase | |||||
It is important to point out that the IFU5 gene can increase the pathogenicity of C. albicans by interacting with the Efg1 gene. Moreover, RTA2 genes increase the resistance of C. albicans to fluconazole, and the IFD6 gene increases the ability of C. albicans to form biofilms [ 45 - 47 ]. The increase in CDR gene mRNA expression is mostly related to CDR1, and CDR2 expression level did not show much difference between resistant and sensitive isolates. [ 28 ]. A study was conducted by Morio et al. in France on fluconazole-resistant C. albicans isolated from hematopoietic stem cell transplant recipients and heart transplant recipients. They found that among the PMA1, ERG11, MDR1, CDR1, and ERG3 genes that were examined, only the ERG11 gene showed increased expression in resistant isolates, compared to sensitive isolates [ 31 ].
These observations are consistent with the findings of a study performed by Eddouzi et al. (2015). In their study, Eddouzi, like Morio, found that the ERG11 level in resistant isolates showed a significant increase. In the aforementioned study, in addition to the ERG11 gene, the expression of the MDR1 gene also increased in resistant isolates [ 34 ].
Expression level of genes involved in C. albicans resistance to azole in diabetic patients
According to a study conducted by Hiyama et al., C. albicans resistance to fluconazole is significantly the result of increased expression of membrane current transporter genes. In contrast to Candida isolates from other underlying diseases, MDR1 showed the highest increase in expression in C. albicans, compared to sensitive species, followed by CDR2, CDR1, and ERG11 [ 38 ].
Expression level of genes involved in C. albicans resistance to azole in autoimmune polyendocrinopathy-candidiasis-ectodermal dystrophy patients
In two studies carried out by Siikala et al. in 2013 and 2010 in Finland on resistant C. albicans isolates obtained from autoimmune polyendocrinopathy-candidiasis-ectodermal dystrophy (APECED) patients, CDR1 and CDR2 genes had higher expression levels. This increase in expression, compared to the wild-type species, is due to the presence of gain-of-function mutations in the regulatory factors of these three genes [ 30 , 32 ].
Expression level of genes involved in C. albicans resistance to azole in immunocompromised patients
In another study conducted in Iran by Alizade et al. on immunocompromised patients, the level of ERG11 gene expression was not significantly different between fluconazole-resistant and fluconazole-sensitive strains [ 37 ].
Discussion
Fluconazole is considered one of the main antifungal drugs for the treatment of Candidiasis [ 37 ]. Despite this, long-term treatment and indiscriminate use of azole family drugs have created isolates resistant to these azoles. These resistant isolates are among the main problems in the treatment of Candidiasis [ 48 ]. Identification of the cause of resistance to azole drugs in clinical isolates of C. albicans can help to provide more appropriate treatment and prevent or control Candidiasis in the future [ 49 ]. Candida albicans cells can develop resistance to fluconazole at the molecular level through various mechanisms, which are explained in detail in the introduction section [ 22 , 50 , 51 ].
Based on the studies conducted since 1995, the CDR1 gene has the highest expression level among the genes involved in resistance, followed by ERG11, MDR1, and CDR2 genes, respectively. The CDR1 gene has the highest expression in HIV-infected, cancer, and APECED patients, making CDR1-mediated resistance the most important resistance mechanism of C. albicans to fluconazole in these patients. However, in transplant patients, the ERG11 gene has the highest expression, and the resistance mechanism in these patients is related to this gene. Moreover, the MDR1 gene showed the highest increase in expression of the isolates obtained from diabetic patients. In fluconazole-resistant C. albicans isolated from HIV-positive patients, the development of resistance depends not only on continuous and intermittent administration of this drug but also on the cumulative dose of the received fluconazole (cumulative dose of fluconazole>10 g) [ 25 ]. Accumulation of this drug is prevented by C. albicans due to a significant increase in the expression level of CDR1 and BENr genes. Both CDR1 and BENr are multidrug transporter genes, each belonging to different classes of transporters [ 16 ].
In cancer patients, accumulation of chemotherapeutic drugs in C. albicans cells stimulates regulatory factors, increases CDR1 and MDR1 gene expression, and ultimately induces resistance. Since the increase in expression of these two genes in cancer and HIV-infected patients causes C. albicans resistance to fluconazole, the isolates in which the MDR1 promoter is more active will grow under fluconazole or other selective pressure and survive longer than susceptible isolates. This provides numerous opportunities to create mutations that confer high levels of drug resistance [ 39 ]. A study of the combined effect of some FDA-approved oncology drugs with fluconazole found that a number of oncology drugs have a negative effect on antifungal activity. Oncological drugs combined with azoles exacerbate antifungal resistance in C. albicansin vitro. These include tamoxifen, epirubicin, idarubicin, nilotinib, ceritinib, daunorubicin, cabazitaxel, and doxorubicin, which are prescribed for lymphoma, prostate cancer, bladder cancer and sarcoma [ 52 ].
Patients with type 2 diabetes are more likely to be affected by internal organ candidiasis [ 53 ]. An increase in the level of glucose, as well as an increase in the serum level of fructose, is one of the important causes of resistance of C. albicansto azole drugs in these patients [ 54 ]. Moreover, according to the study performed by Hiyama et al., an increase in urine glucose concentration promotes the growth of C. albicans and also significantly increases the expression of genes involved in C. albicans resistance to fluconazole, especially CDR2 and MDR1. Increased expression of these two genes plays an important role in resistance to fluconazole in Candida species isolated from these patients [ 38 ].
In a study published in 2009, Uittamo et al. found that C. albicans isolated from APECED patients were able to produce high levels of carcinogenic acetaldehyde in vitro. In C. albicans, alcohol dehydrogenase, encoded by ADH1, catalyzes the oxidation of ethanol to acetaldehyde. Expression of ADH1 is necessary for the production of ADH and acetaldehyde from ethanol [ 55 ]. According to the findings of a study performed by Sikala in 2013, the expression of the ADH1 gene is strongly increased in isolates with low CDR1 and CDR2 expression levels. In other words, the expression levels of the ADH1, CDR1, and CDR2 genes have an inverse relationship. Most fluconazole-resistant isolates of C. albicans have highly increased expression levels of CDR1 and CDR2, while ADH1 has the lowest expression level [ 32 ]. This important finding demonstrates the relationship between the acetaldehyde metabolism genes of C. albicans in these patients and azole resistance.
It is important to mention that in a number of studies, the overexpression of genes responsible for resistance has been observed only in some isolates and not in all isolates. Since the ERG11 gene has been investigated in several studies, more aspects of this gene have been identified, compared to other major resistance-causing genes. It should be noted that fluconazole resistance in C. albicans is the result of different mechanisms controlled by different genes, with the ERG11 gene being only one of them. One or more other genes may also be involved in creating the resistant phenotype.
Financial limitations and lack of advanced laboratory facilities in underdeveloped or less developed countries have led researchers to select fewer genes for study, and sometimes these selected genes do not show overexpression in both resistant and susceptible isolates. In this case, the resistance mechanism may be related to other genes that the researcher has not studied. For example, in a study conducted by Alizadeh et al. in Iran, only the ERG11 gene was examined in resistant isolates of C. albicans isolated from immunocompromised patients. Finally, it was found that ERG11 was not over-expressed in the resistant and sensitive isolates.
Extensive investigation of different genes involved in resistance, using molecular techniques, such as microarray and RNA-seq, can reveal new and broader aspects of their role. In isolates obtained from HIV-infected patients with candidiasis, the CDR1 gene was the most highly expressed gene, while in transplant patients, the ERG11 gene was the most highly expressed gene. This difference in resistance gene expression in isolates from patients with other underlying conditions, as mentioned in the results section, also exists and may have several potential causes.
Conclusion
Genotypic differences between isolates from various parts of the world, the type of underlying disease, drug interactions between the antifungals and medications the individual was taking for the underlying condition, as well as the dosage and duration of the antifungals, may play an important role in determining the resistance mechanism of C. albicans. According to the conducted studies, it can be said that the expression level of fluconazole resistance genes varies in C. albicans species isolated from individuals with different underlying diseases. Nevertheless, to better clarify this issue, more studies need to be conducted with a larger number of fluconazole-resistant isolates and a larger number of genes.
Acknowledgments
The authors sincerely thank all the people who helped in conducting the current study and also Ahvaz Jundishapur University of Medical Sciences, Ahvaz, Iran, for their cooperation in this study.
Authors’ contributions
M. F. conceived and designed the study and provided final approval for the version to be published, A. H., M. M., and J. J. searched the literature; A. H. and M. M. extracted the data. A. H. and M. T. A. wrote the manuscript. A. H. prepared figures 1-3. All authors have read, critically revised, and approved the final manuscript.
Conflicts of interest
The authors have no conflicts of interest to disclose. All authors have approved that the final article was true and included in the disclosure.
Financial disclosure
This work was supported by Ahvaz Jundishapur University of Medical Sciences (Research code: U-02108).
References
- Vila T, Sultan AS, Montelongo-Jauregui D, Jabra-Rizk MA. Oral candidiasis: a disease of opportunity. J Fungi (Basel). 2020 ; 6(1):15.
- Pappas PG, Lionakis MS, Arendrup MC, Ostrosky-Zeichner L, Kullberg BJ. Invasive candidiasis. Nat Rev Dis Primers. 2018 ; 4(1):18026.
- Aboualigalehdari E, Tahmasebi Birgani M, Fatahinia M, Hosseinzadeh M. Oral colonization by Candida species and associated factors in HIV-infected patients in Ahvaz, southwest Iran. Epidemiol Health. 2020; 42:e2020033.
- Mohamed AA, Lu XL, Mounmin FA. Diagnosis and treatment of esophageal candidiasis: current updates. Can J Gastroenterol Hepatol. 2019; 2019:3585136.
- Bhattacharya S, Sae-Tia S, Fries BC. Candidiasis and mechanisms of antifungal resistance. Antibiotics (Basel). 2020; 9(6):312.
- Carvalho VO, Okay TS, Melhem MS, Szeszs MW, del Negro GM. The new mutation L321F in Candida albicans ERG11 gene may be associated with fluconazole resistance. Rev Iberoam Micol. 2013; 30(3):209-12.
- Dannaoui É. Résistance des Candida aux antifongiques: détection et mécanismes. Revue Francophone des Laboratoires. 2013; 2013(450):71-7.
- Wang H, Kong F, Sorrell TC, Wang B, McNicholas P, Pantarat N, et al. Rapid detection of ERG11 gene mutations in clinical Candida albicans isolates with reduced susceptibility to fluconazole by rolling circle amplification and DNA sequencing. BMC Microbiol. 2009 ; 9:167.
- Sasse C, Schillig R, Dierolf F, Weyler M, Schneider S, Mogavero S, et al. The transcription factor Ndt80 does not contribute to Mrr1-, Tac1-, and Upc2-mediated fluconazole resistance in Candida albicans. PloS one. 2011; 6(9):e25623.
- Heilmann CJ, Schneider S, Barker KS, Rogers PD, Morschhauser J. An A643T mutation in the transcription factor Upc2p causes constitutive ERG11 upregulation and increased fluconazole resistance in Candida albicans. Antimicrob Agents Chemother. 2010; 54(1):353-9.
- Xu J, Liu R, Sun F, An L, Shang Z, Kong L, et al. Eucalyptal D enhances the antifungal effect of fluconazole on fluconazole-Resistant Candida albicans by competitively inhibitingb efflux pump. Front Cell Infect Microbiol. 2019; 9:211.
- Zhang JY, Liu JH, Liu FD, Xia YH, Wang J, Liu X, et al. Vulvovaginal candidiasis: species distribution, fluconazole resistance and drug efflux pump gene overexpression. Mycoses. 2014; 57(10):584-91.
- Miyazaki T, Miyazaki Y, Izumikawa K, Kakeya H, Miyakoshi S, Bennett JE, et al. Fluconazole treatment is effective against a Candida albicans erg3/erg3 mutant in vivo despite in vitro resistance. Antimicrob Agents Chemother. 2006; 50(2):580-6.
- Manastır L, Ergon MC, Yücesoy M. Investigation of mutations in Erg11 gene of fluconazole resistant Candida albicans isolates from Turkish hospitals. Mycoses. 2011; 54(2):99-104.
- Bandara H, Wood DLA, Vanwonterghem I, Hugenholtz P, Cheung BPK, Samaranayake LP. Fluconazole resistance in Candida albicans is induced by Pseudomonas aeruginosa quorum sensing. Sci Rep. 2020; 10(1):7769.
- Sanglard D, Kuchler K, Ischer F, Pagani JL, Monod M, Bille J. Mechanisms of resistance to azole antifungal agents in Candida albicans isolates from AIDS patients involve specific multidrug transporters. Antimicrob Agents Chemother. 1995; 39(11):2378-86.
- White TC. Increased mRNA levels of ERG16, CDR, and MDR1 correlate with increases in azole resistance in Candida albicans isolates from a patient infected with human immunodeficiency virus. Antimicrob Agents Chemother. 1997; 41(7):1482-7.
- Franz R, Michel S, Morschhauser J. A fourth gene from the Candida albicans CDR family of ABC transporters. Gene. 1998 ; 220(1-2):91-8.
- Lopez-Ribot JL, McAtee RK, Lee LN, Kirkpatrick WR, White TC, Sanglard D, et al. Distinct patterns of gene expression associated with development of fluconazole resistance in serial Candida albicans isolates from human immunodeficiency virus-infected patients with oropharyngeal candidiasis. Antimicrob Agents Chemother. 1998; 42(11):2932.
- Franz R, Kelly SL, Lamb DC, Kelly DE, Ruhnke M, Morschhauser J. Multiple molecular mechanisms contribute to a stepwise development of fluconazole resistance in clinical Candida albicans strains. Antimicrob Agents Chemother. 1998; 42(12):3065-72.
- Maesaki S, Marichal P, Vanden Bossche H, Sanglard D, Kohno S. Rhodamine 6G efflux for the detection of CDR1-overexpressing azole-resistant Candida albicans strains. J Antimicrob Chemother. 1999; 44(1):27-31.
- Perea S, Lopez-Ribot JL, Kirkpatrick WR, McAtee RK, Santillan RA, Martinez M, et al. Prevalence of molecular mechanisms of resistance to azole antifungal agents in Candida albicans strains displaying high-level fluconazole resistance isolated from human immunodeficiency virus-infected patients. Antimicrob Agents Chemother. 2001; 45(10):2676-84.
- Maebashi K, Niimi M, Kudoh M, Fischer FJ, Makimura K, Niimi K, et al. Mechanisms of fluconazole resistance in Candida albicans isolates from Japanese AIDS patients. J Antimicrob Chemother. 2001; 47(5):527-36.
- Rogers PD, Barker KS. Evaluation of differential gene expression in fluconazole-susceptible and -resistant isolates of Candida albicans by cDNA microarray analysis. Antimicrob Agents Chemother. 2002; 46(11):3412-17.
- Martinez M, Lopez-Ribot JL, Kirkpatrick WR, Bachmann SP, Perea S, Ruesga MT, et al. Heterogeneous mechanisms of azole resistance in Candida albicans clinical isolates from an HIV-infected patient on continuous fluconazole therapy for oropharyngeal candidosis. J Antimicrob Chemother. 2002; 49(3):515-24.
- Goldman GH, da Silva Ferreira ME, dos Reis Marques E, Savoldi M, Perlin D, Park S, et al. Evaluation of fluconazole resistance mechanisms in Candida albicans clinical isolates from HIV-infected patients in Brazil. Diagn Microbiol Infect Dis. 2004; 50(1):25-32.
- Ribeiro MA, Paula CR, John R, Perfect JR, Cox GM. Phenotypic and genotypic evaluation of fluconazole resistance in vaginal Candida strains isolated from HIV-infected women from Brazil. Med Mycol. 2005; 43(7):647-50.
- Xu Z, Zhang LX, Zhang JD, Cao YB, Yu YY, Wang DJ, et al. cDNA microarray analysis of differential gene expression and regulation in clinically drug-resistant isolates of Candida albicans from bone marrow transplanted patients. Int J Med Microbiol. 2006; 296(6):421-34.
- Dunkel N, Liu TT, Barker KS, Homayouni R, Morschhauser J, Rogers PD. A gain-of-function mutation in the transcription factor Upc2p causes upregulation of ergosterol biosynthesis genes and increased fluconazole resistance in a clinical Candida albicans isolate. Eukaryot Cell. 2008; 7(7):1180-90.
- Siikala E, Rautemaa R, Richardson M, Saxen H, Bowyer P, Sanglard D. Persistent Candida albicans colonization and molecular mechanisms of azole resistance in autoimmune polyendocrinopathy–candidiasis–ectodermal dystrophy (APECED) patients. J Antimicrob Chemother. 2010; 65(12):2505-13.
- Morio F, Pagniez F, Lacroix C, Miegeville M, Le Pape P. Amino acid substitutions in the Candida albicans sterol Δ5, 6-desaturase (Erg3p) confer azole resistance: characterization of two novel mutants with impaired virulence. J Antimicrob Chemother. 2012; 67(9):2131-38.
- Siikala E, Bowyer P, Richardson M, Saxen H, Sanglard D, Rautemaa R. ADH1 expression inversely correlates with CDR1 and CDR2 in Candida albicans from chronic oral candidosis in APECED (APS-I) patients. FEMS Yeast Res. 2011; 11(6):494-8.
- Morio F, Pagniez F, Besse M, Gay-andrieu F, Miegeville M, Le Pape P. Deciphering azole resistance mechanisms with a focus on transcription factor-encoding genes TAC1, MRR1 and UPC2 in a set of fluconazole-resistant clinical isolates of Candida albicans. Int J Antimicrob Agents. 2013; 42(5):410-5.
- Eddouzi J, Parker JE, Vale-Silva LA, Coste A, Ischer F, Kelly S, et al. Molecular mechanisms of drug resistance in clinical Candida species isolated from Tunisian hospitals. Antimicrob Agents Chemother. 2013; 57(7):3182-93.
- Rosana Y, Yasmon A, Lestari DC. Overexpression and mutation as a genetic mechanism of fluconazole resistance in Candida albicans isolated from human immunodeficiency virus patients in Indonesia. J Med Microbiol. 2015; 64(9):1046-52.
- Salari S, Khosravi AR, Mousavi SA, Nikbakht-Brojeni GH. Mechanisms of resistance to fluconazole in Candida albicans clinical isolates from Iranian HIV-infected patients with oropharyngeal candidiasis. J Mycol Med. 2016; 26(1):35-41.
- Alizadeh F, Khodavandi A, Zalakian S. Quantitation of ergosterol content and gene expression profile of ERG11 gene in fluconazole-resistant Candida albicans. Curr Med Mycol. 2017; 3(1):13-9.
- Hiyama Y, Sato T, Takahashi S, Yamamoto S, Ogasawara N, Masumori N, et al. Reduction of susceptibility to azoles and 5-fluorocytosine and growth acceleration in Candida albicans in glucosuria. Diagn Microbiol Infect Dis. 2022; 102(1):115556.
- Maheronnaghsh M, Teimoori A, Dehghan P, Fatahinia M. The evaluation of the overexpression of the ERG-11, MDR-1, CDR-1, and CDR-2 genes in fluconazole-resistant Candida albicans isolated from Ahvazian cancer patients with oral candidiasis. J Clin Lab Anal. 2022; 36(2):e24208.
- Jahanshiri Z, Manifar S, Arastehnazar F, Hatami F, Lotfali E. Azole resistance in Candida albicans isolates from oropharyngeal candidiasis is associated with ERG11 mutation and efflux overexpression. Jundishapur J Microbiol. 2022; 15(9): e131046.
- Erfaninejad M, Zarei Mahmoudabadi A, Maraghi E, Hashemzadeh M, Fatahinia M. Epidemiology, prevalence, and associated factors of oral candidiasis in HIV patients from southwest Iran in post-highly active antiretroviral therapy era. Front Microbiol. 2022; 13:983348.
- Sardari A, Zarrinfar H, Mohammadi R. Detection of ERG11 point mutations in Iranian fluconazole-resistant Candida albicans isolates. Curr Med Mycol. 2019; 5(1):7-14.
- Hampe IAI, Friedman J, Edgerton M, Morschhauser J. An acquired mechanism of antifungal drug resistance simultaneously enables Candida albicans to escape from intrinsic host defenses. PLoS Pathog. 2017; 13(9):e1006655.
- Zhang H, Xu Q, Li S, Ying Y, Zhang Z, Zeng L, et al. Gene expression analysis of key players associated with fluconazole resistance in Candida albicans. Jundishapur J Microbiol. 2019; 12(7): e88521.
- Rastogi SK, van Wijlick L, Ror S, Lee KK, Román E, Agarwal P, et al. Ifu5, a WW domain‐containing protein interacts with Efg1 to achieve coordination of normoxic and hypoxic functions to influence pathogenicity traits in Candida albicans. Cell Microbiol. 2020; 22(2):e13140.
- Jia XM, Ma ZP, Jia Y, Gao PH, Zhang JD, Wang Y, et al. RTA2, a novel gene involved in azole resistance in Candida albicans. Biochem Biophys Res Commun. 2008; 373(4):631-6.
- Li Y, Li DD, Wang Y, Liu LC, Huang H, Fu ST, et al. Overexpression of IFD6 in Candida albicans promotes biofilm formation. Acade J Secon Military Med Unive. 2010; 12:599-603.
- Boken DJ, Swindells S, Rinaldi MG. Fluconazole-resistant Candida albicans. Clin Infect Dis. 1993; 17(6):1018-1021.
- Casalinuovo IA, Di Francesco P, Garaci E. Fluconazole resistance in Candida albicans: a review of mechanisms. Eur Rev Med Pharmacol Sci. 2004; 8(2):69-77.
- White TC, Holleman S, Dy F, Mirels LF, Stevens DA. Resistance mechanisms in clinical isolates of Candida albicans. Antimicrob Agents Chemother. 2002; 46(6):1704-13.
- Marichal P, Koymans L, Willemsens S, Bellens D, Verhasselt P, Luyten W, et al. Contribution of mutations in the cytochrome P450 14α-demethylase (Erg11p, Cyp51p) to azole resistance in Candida albicans. Microbiology. 1999; 145(10):2701-13.
- Butts A, Reitler P, Ge W, Fortwendel JR, Palmer GE. Commonly used oncology drugs decrease antifungal effectiveness against Candida and Aspergillus species. Antimicrob Agents Chemother. 2018; 62(7):e00504-e00518.
- Martinez RF, Jaimes-Aveldanez A, Hernandez-Perez F, Arenas R, Miguel GF. Oral Candida spp carriers: its prevalence in patients with type 2 diabetes mellitus. An Bras Dermatol. 2013; 88(2):222-5.
- Mandal SM, Mahata D, Migliolo L, Parekh A, Addy PS, Mandal M, et al. Glucose directly promotes antifungal resistance in the fungal pathogen, Candida spp. J Biol Chem. 2014; 289(37):25468-73.
- Uittamo J, Siikala E, Kaihovaara P, Salaspuro M, Rautemaa R. Chronic candidosis and oral cancer in APECED‐patients: production of carcinogenic acetaldehyde from glucose and ethanol by Candida albicans. Int J Cancer. 2009; 124(3):754-6.


